
Abdominal Bloating and Visible Distension: Could It Be Abdominophrenic Dyssynergia (APD)?
Why your abdomen can become visibly larger and what may help
Medically reviewed by Dr Douglas Samuel, Gastroenterologist · September 2026
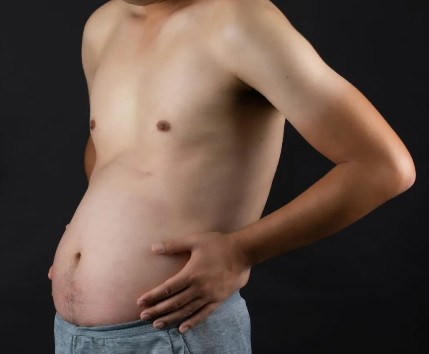
Abdominal bloating and visible distension: could it be APD?
If your abdomen looks and feels larger, the first useful step is working out what kind of change it is, because that points to different causes and different treatment.
Bloating is what you feel: fullness, pressure or tightness. Visible distension is when your abdomen actually looks larger than usual.
An abdomen that is simply prominent most of the time, and much the same on waking as after meals, may not be what doctors mean by “distension” at all.
This page helps you tell these apart and explains one mechanism, abdominophrenic dyssynergia (APD), that can drive genuine, visible, come-and-go abdominal distension.
If you wake up relatively flat, drink a glass of water and suddenly look nine months pregnant, help may be on its way.
What is Abdominophrenic Dyssynergia (APD)?
Abdominophrenic dyssynergia (APD) is a proposed mechanism that can cause episodes of visible abdominal distension. It describes abnormal coordination between the diaphragm and abdominal wall, rather than a disease of the bowel itself.
Many people with long-standing bloating have more than one contributing mechanism. APD may explain the visible change in abdominal shape, while constipation, irritable bowel syndrome, functional dyspepsia, food fermentation and visceral hypersensitivity may contribute to fullness, pressure, pain or gas.
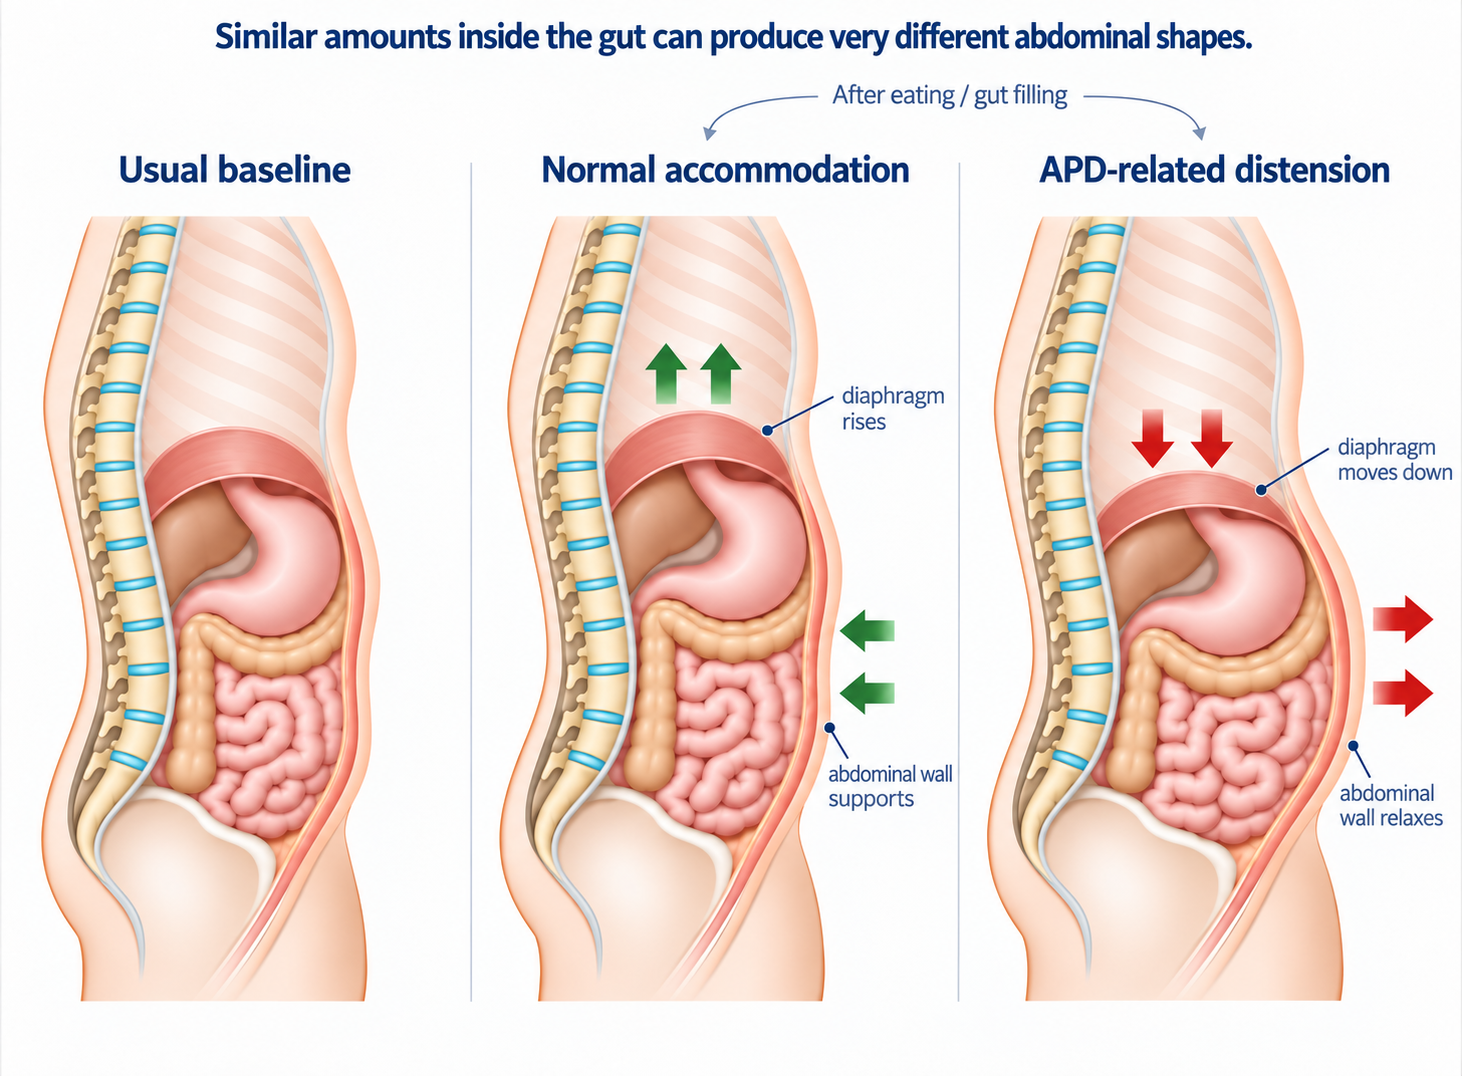
Normally, when the gut fills after eating, the body accommodates the extra volume without marked forward protrusion. The diaphragm relaxes and moves upwards while the abdominal wall maintains support, allowing the abdomen to accommodate the contents with relatively little change in shape.
In APD, this pattern is altered. The diaphragm contracts and moves downward while the front abdominal wall relaxes and moves outward. This shifts the abdominal contents forwards and can make the abdomen visibly larger without a large increase in intestinal gas. The change is often noticed after meals or as the day progresses, although the timing varies from person to person.
APD is most likely to be relevant when the abdomen changes visibly from its usual baseline during episodes. People may notice:
- the abdomen becoming noticeably larger during or after meals, or later in the day;
- clothing becoming tighter during these episodes;
- pressure, fullness or discomfort accompanying the visible change;
- the abdomen becoming smaller again between episodes, sometimes overnight or by morning; and
- a repeatable pattern of visible distension that seems out of proportion to the amount eaten.
APD describes a proposed physical pattern involving gut–brain signalling and the muscles that shape the abdomen. It is not imagined, and it does not mean symptoms are simply caused by anxiety.
APD is only one possible mechanism. Bloating and visible distension can also occur with constipation, IBS, functional dyspepsia, food fermentation and visceral hypersensitivity. A persistently prominent abdomen that changes little from its baseline may instead reflect the abdominal wall, posture or body shape, although these patterns can coexist.
What’s the difference between bloating, distension and structural abdominal prominence?
what you feel
Bloating
Fullness, pressure or tightness. Can occur with little or no visible change in size.
episodic visible change
Visible distension
A small change in gas, but a large change in shape. Often larger after meals or later in the day, and smaller by morning. This is the pattern APD can drive.
much the same all the time
Persistent (structural) prominence
Prominent on waking and after meals alike. More often reflects the abdominal wall, posture or body shape than the gut.
each dot represents gut gas
These are different things, but they often overlap. More than one can be present at the same time.
Bloating is the sensation of fullness, pressure, tightness, trapped gas or swelling. Distension is a visible increase in the size of the abdomen compared with its usual baseline. They often occur together, but they are not the same symptom: you can feel markedly bloated with little visible change, or look visibly larger with relatively little discomfort.
Some visible change after meals, or when standing rather than lying, is ordinary and normal. The body accommodates food and gas with some change in shape, and how noticeable this is varies from person to person. A mild change that does not trouble you does not need treatment.
The more useful question is not how large the abdomen looks, but whether it is changing from your own baseline. An abdomen that is already prominent on waking and changes little after meals or through the day is better thought of as persistent abdominal prominence, rather than distension alone. That distinction matters because persistent prominence can have different causes and may need a different approach. It can also coexist with genuine episodes of distension.
APD is one possible mechanism for visible change: the diaphragm moves downward while the front abdominal wall relaxes and moves outward, altering the shape of the abdomen without a large increase in intestinal gas.
Other contributors to bloating or distension include constipation, IBS, functional dyspepsia, food-related fermentation or intolerance, and visceral hypersensitivity. A persistently prominent abdomen, by contrast, may reflect the abdominal wall, posture or body shape rather than the gut. Stress and anxiety can amplify gut sensations and how intrusive they feel, but they do not mean the symptoms are imagined.

How Is APD Assessed?
There is currently no routine test or accepted set of clinical criteria that confirms APD.
APD is a proposed mechanism that may be considered when there are reproducible episodes of visible abdominal distension, particularly when the abdomen becomes larger after meals or later in the day and no other important cause is apparent after appropriate assessment.
Assessment may include:
- the pattern and timing of visible distension;
- whether the abdomen returns towards its usual baseline;
- associated bloating, fullness, pain or bowel symptoms;
- examination of the abdomen and abdominal wall;
- checking for warning symptoms; and
- targeted investigation when another condition needs to be excluded.
If the history and examination are reassuring and there are no warning features, extensive blood tests, scans or endoscopy are usually not needed simply because bloating or distension is present. Tests are targeted when another condition needs to be excluded.
Research studies have measured APD using muscle recordings, thoracoabdominal movement sensors and imaging during episodes of distension. These methods are not routinely available as diagnostic tests.
Improvement with APD retraining does not prove that APD was the cause.
When APD May Be Contributing
APD is most relevant when there are episodes of visible abdominal distension rather than simply a persistently prominent abdomen.
Clues may include:
- the abdomen becoming visibly larger after meals or later in the day;
- a reproducible change from the person’s usual abdominal shape;
- improvement overnight or on waking;
- distension that seems disproportionate to the amount eaten; and
- no other explanation found after appropriate assessment.
APD can coexist with constipation, IBS, functional dyspepsia, food-related fermentation or visceral hypersensitivity.
A persistently prominent abdomen that changes little through the day is less typical of the pattern studied in APD biofeedback trials.
Why does APD happen to me?
We do not yet know exactly why this develops.
APD appears to be an abnormal, potentially learned coordination pattern between the diaphragm, abdominal wall and rib cage. Gut sensations such as fullness, bloating or distension can trigger the wrong muscular response. Instead of the diaphragm relaxing and the abdominal wall supporting the abdomen, the diaphragm contracts and moves down, the rib cage and intercostal muscles become more active, and the abdominal wall relaxes.
Why this pattern develops in the first place is uncertain. Abdominal surgery, Caesarean section, pregnancy and childbirth, posture and habitual breathing patterns have all been proposed as possible contributors, but none has been proven to cause APD.
The encouraging part is that APD is not a damaged or weak diaphragm. It is a coordination problem that can be retrained.
What your body has learned, it can unlearn and then learn to do differently.
Could it be something else?
APD is only one possible contributor to bloating or visible distension. Other common possibilities include:
- constipation or incomplete emptying;
- IBS, functional dyspepsia or other disorders of gut–brain interaction (DGBIs);
- food-related fermentation or intolerance;
- visceral hypersensitivity;
- pelvic-floor dysfunction; and
- abdominal-wall or structural problems (see below).
The pattern of symptoms usually gives more useful clues than trying to test for every possibility.
Treating APD and common overlapping conditions
There is no single treatment for everyone with bloating or visible distension.
Bloating and distension are not always completely curable. For some people, they can affect clothing, eating, work, exercise and social life, and embarrassment about abdominal appearance can become severe enough that they avoid going out.
The aim is to identify the main drivers, reduce how often and how severely symptoms occur, and help you get back to everyday life. Even when symptoms do not disappear completely, worthwhile improvement is often possible.
Treatment works best when it targets the main driver or drivers of the symptoms.
For some people, APD movement retraining is the main treatment. For others, constipation, pelvic-floor dysfunction, food-related fermentation, functional dyspepsia, visceral hypersensitivity or another contributor may need more attention.
Several mechanisms can occur together, so treatment is often best introduced step by step.
APD movement retraining
APD retraining aims to change the coordination between the lower chest, diaphragm and abdominal wall.
The key movement is:
Lower chest gently up, abdomen gently in.
I use the term Pendulum Breathing to describe this full movement.
As the lower chest moves gently up, the abdomen moves gently in. On the return movement, the chest moves gently down while the abdominal wall relaxes and the belly is allowed to soften and fall naturally with gravity rather than being pushed out.
Breathing should remain comfortable throughout.
Pendulum Breathing is not the same as conventional diaphragmatic or “belly” breathing. Diaphragmatic breathing can be useful for other reasons, but APD retraining teaches a different pattern of chest and abdominal movement.
The strongest published evidence comes from supervised biofeedback studies in people with recurrent visible abdominal distension. In these studies, sensors allowed patients to see in real time how their chest and abdominal wall were moving and learn to reverse the abnormal pattern.
A 2025 randomised placebo-controlled study, presented in abstract form, also reported benefit from clinician-guided retraining without sensors, using explanation, audiovisual support and hands-on guidance followed by daily home practice. This suggests that specialised motion sensors may not always be necessary, although the treatment was still supervised and the evidence remains preliminary.
The movement can also be taught by an experienced doctor or therapist. Some people can produce a visible reduction in distension during a supervised session, although learning to reproduce the movement naturally and consistently usually takes practice.
The home program on this website adapts this movement pattern for self-guided practice. It has not been shown to be equivalent to either sensor-guided biofeedback or supervised clinician-guided retraining, and improvement with the exercises does not by itself confirm a diagnosis of APD.
Choosing where to start
You do not need to treat everything at once. A practical approach is:
- Visible episodes of distension that change from your usual baseline and come and go: consider APD movement retraining.
- Constipation or incomplete emptying: improve bowel function and consider pelvic-floor assessment when appropriate.
- Clear food-related symptoms: consider structured dietary assessment rather than broad or prolonged food restriction.
- Early fullness, nausea or upper abdominal discomfort: consider functional dyspepsia and other upper-gut mechanisms.
- Pain, pressure or heightened awareness of digestion: consider treatments directed at visceral hypersensitivity and gut–brain signalling.
- A focal bulge, or an abdomen that remains prominent rather than changing through the day: consider an abdominal-wall or structural cause.
- Several overlapping patterns: introduce treatments gradually so you can tell what is helping.
The goal is not to make every abdomen flat, achieve any particular body shape, eliminate every normal digestive sensation or prevent normal changes in abdominal shape after eating.
Ideas about what an abdomen should look like vary between people and cultures. The clinical question is whether there are troublesome symptoms or a meaningful change from your own baseline.
The goal is to reduce troublesome symptoms and help you eat, move and get on with daily life more comfortably.
The APD Movement Training Program
The strongest treatment evidence for APD comes from supervised biofeedback studies in people with recurrent episodes of visible abdominal distension.
During these studies, sensors showed participants how their lower chest and abdominal wall were moving. They learned to change this movement pattern and then practised it at home.
A 2025 randomised study also found benefit from clinician-guided training without sensors, using explanation, audiovisual instruction and hands-on guidance followed by home practice. This is encouraging, but a wholly self-guided web program has not been shown to be equivalent, and independent replication is still awaited.
The four-week program on this website is a practical self-guided adaptation of that movement.
It is not the same as the sensor- or clinician-guided treatment used in the clinical trials, and the self-guided version has not been shown to produce the same results.
It is most relevant if your abdomen becomes visibly larger during episodes. The research has not established that APD retraining changes a persistently prominent resting abdominal shape.
What If APD Movement Training Does Not Help?
Not everyone with bloating or visible distension has APD as the main mechanism, and not everyone with APD will respond to self-guided movement training.
If you are confident that you are performing the movement correctly but there is little improvement after repeated practice, simply practising harder is unlikely to be the answer. Another mechanism may be contributing and may need more attention.
If the technique itself remains uncertain, a clinician or physiotherapist familiar with APD may help check the movement. Where available, sensor-guided biofeedback is the approach closest to that used in the clinical trials.
Improvement should be judged over repeated episodes and over time, rather than by whether you can make the abdomen flatten immediately during a single episode.
Other Things That May Help
APD movement retraining is only one part of managing bloating and distension. The sections below cover other common contributors and practical treatment options.
Which are most relevant depends on your symptoms. You do not need to try everything.
When to Seek Medical Advice
Most bloating and distension is not caused by serious disease, but new, persistent or progressive symptoms should not automatically be assumed to be APD.
Seek medical assessment if symptoms are associated with:
- unexplained weight loss;
- persistent or recurrent vomiting;
- gastrointestinal bleeding or black stools;
- iron-deficiency anaemia;
- progressive difficulty swallowing;
- persistent severe or localised abdominal pain;
- fever;
- a new or progressively enlarging abdominal mass;
- new or progressively increasing persistent abdominal swelling; or
- a substantial unexplained change in bowel habit.
Severe cramping abdominal pain with persistent vomiting and inability to pass stool or gas may indicate bowel obstruction and needs urgent medical assessment.
The need for investigation depends on age, medical history, examination findings and the pattern of symptoms.
If worry about your abdomen is affecting how you eat, exercise or feel day to day, that is also worth discussing with your doctor.
Frequently Asked Questions
Does bloating mean I have too much gas?
Not necessarily. Bloating is a sensation, and visible distension can occur without a large increase in intestinal gas. Gut sensitivity, bowel contents, fermentation, muscle responses and abdominal-wall mechanics can all contribute.
Is APD caused by anxiety?
No. APD describes a proposed physical pattern of thoracoabdominal movement. Stress and anxiety can influence gut–brain signalling and symptom severity, but that does not mean the symptoms are imagined or simply caused by anxiety.
Does a normal CT, gastroscopy or colonoscopy rule out APD?
No. These investigations are designed mainly to look for structural disease. APD describes a proposed thoracoabdominal movement pattern, and there is currently no routine diagnostic test that confirms it.
If my abdomen is always prominent, is that APD?
Not necessarily. APD research has mainly studied people with episodes in which the abdomen becomes visibly larger than its usual baseline. A persistently prominent abdomen that changes little through the day may instead reflect body shape, fat distribution, posture, abdominal-wall mechanics or another cause. These patterns can also coexist.
If I am flatter in the morning and much larger later, does that prove I have APD?
No. That pattern is compatible with the episodic visible distension studied in APD research, but it is not specific enough to diagnose APD. Meal volume, constipation, fermentation and other mechanisms can produce a similar pattern.
Should the exercises flatten my abdomen straight away?
No. Immediate visible flattening has not been established as a test of successful APD treatment. The more useful question is whether troublesome episodes become less frequent, less severe or easier to manage over time.
If the exercises help, does that prove I have APD?
No. Improvement can suggest that changing thoracoabdominal coordination is useful for you, but response to an exercise is not a diagnostic test for APD. Similarly, failure to improve does not prove that APD is absent.
Can I have APD and IBS, constipation, SIBO or functional dyspepsia at the same time?
Yes. APD describes one mechanism that can contribute to visible abdominal distension. IBS, constipation, functional dyspepsia, food fermentation, small intestinal bacterial overgrowth (SIBO) and pelvic-floor problems can coexist with it. Finding one does not prove or exclude another. Treatment works best when it targets the mechanisms that are actually contributing to your symptoms.
Should I hold my breath or suck my stomach in during Pendulum Breathing?
Not for this self-guided program. Keep breathing comfortably and use only gentle abdominal-wall activation. Do not forcefully suck the abdomen in, brace, strain or perform a Valsalva manoeuvre.
The supervised research protocol also allowed a closed-airway version of the alternating movement, but deliberate breath-holding has not been shown to be necessary or better for self-guided training.
Why can APD make you feel short of breath?
When distension is severe, breathing can feel tight, laboured or as though you cannot take a satisfying deep breath.
In APD, the diaphragm contracts and moves down while the muscles between the ribs can become more active and lift the chest. This can leave the chest relatively expanded and make breathing feel more effortful.
Researchers have described the mechanics as resembling the hyperinflation seen in severe asthma, but there is an important difference: APD does not itself imply narrowing of the airways. The problem is abnormal coordination of the diaphragm, abdominal wall and rib cage rather than obstruction to airflow.
Because breathlessness has many causes, new, severe or unexplained breathing symptoms should be assessed in their own right and not simply assumed to be APD.
Evidence and Further Reading
The evidence base for APD includes physiological, imaging and electromyography studies, expert review, consensus guidance and randomised trials of biofeedback-based retraining. Preliminary research has also examined clinician-guided retraining without specialised motion sensors.
- Moshiree B, Drossman D, Shaukat A. AGA Clinical Practice Update on Evaluation and Management of Belching, Abdominal Bloating, and Distention: Expert Review (opens in new tab). Gastroenterology. 2023;165(3):791-800.e3. doi:10.1053/j.gastro.2023.04.039.
- Damianos JA, Tomar SK, Azpiroz F, Barba E. Abdominophrenic Dyssynergia: A Narrative Review (opens in new tab). Am J Gastroenterol. 2023;118(1):41-45. doi:10.14309/ajg.0000000000002044.
- Villoria A, Azpiroz F, Burri E, et al. Abdomino-phrenic dyssynergia in patients with abdominal bloating and distension (opens in new tab). Am J Gastroenterol. 2011;106(5):815-819. doi:10.1038/ajg.2010.408.
- Burri E, Cisternas D, Villoria A, et al. Accommodation of the abdomen to its content: integrated abdomino-thoracic response (opens in new tab). Neurogastroenterol Motil. 2012;24(4):312-e162. doi:10.1111/j.1365-2982.2011.01846.x.
- Barba E, Burri E, Accarino A, et al. Abdominothoracic mechanisms of functional abdominal distension and correction by biofeedback (opens in new tab). Gastroenterology. 2015;148(4):732-739. doi:10.1053/j.gastro.2014.12.006.
- Barba E, Accarino A, Azpiroz F. Correction of Abdominal Distention by Biofeedback-Guided Control of Abdominothoracic Muscular Activity in a Randomized, Placebo-Controlled Trial (opens in new tab). Clin Gastroenterol Hepatol. 2017;15(12):1922-1929. doi:10.1016/j.cgh.2017.06.052.
- Barba E, Burri E, Quiroga S, et al. Visible abdominal distension in functional gut disorders: Objective evaluation (opens in new tab). Neurogastroenterol Motil. 2023;35(2):e14466. doi:10.1111/nmo.14466.
- Barba E, Livovsky DM, Accarino A, Azpiroz F. Thoracoabdominal Wall Motion-Guided Biofeedback Treatment of Abdominal Distention: A Randomized Placebo-Controlled Trial (opens in new tab). Gastroenterology. 2024;167(3):538-546.e1. doi:10.1053/j.gastro.2024.03.005.
- Melchior C, Hammer H, Bor S, et al. European Consensus on Functional Bloating and Abdominal Distension: ESNM/UEG Recommendations for Clinical Management (opens in new tab). United European Gastroenterol J. 2025;13(9):1613-1651. doi:10.1002/ueg2.70098.
- Barber C, Pribic T, Serra J, Azpiroz F. Non-instrumental biofeedback for abdominal distension: placebo controlled trial (opens in new tab). Neurogastroenterol Motil. 2025; abstract NGS21829-94. doi:10.1111/nmo.70126.