
A practical guide to using colestyramine (Questran®)
Cholestyramine helps rebalance bowel function by binding bile acids inside the intestine. When used correctly and given enough time, it is an effective stool-forming regulator, particularly for bile acid-related diarrhoea and for improving bowel control in people with loose bowel motions, leakage or incontinence.
The short version
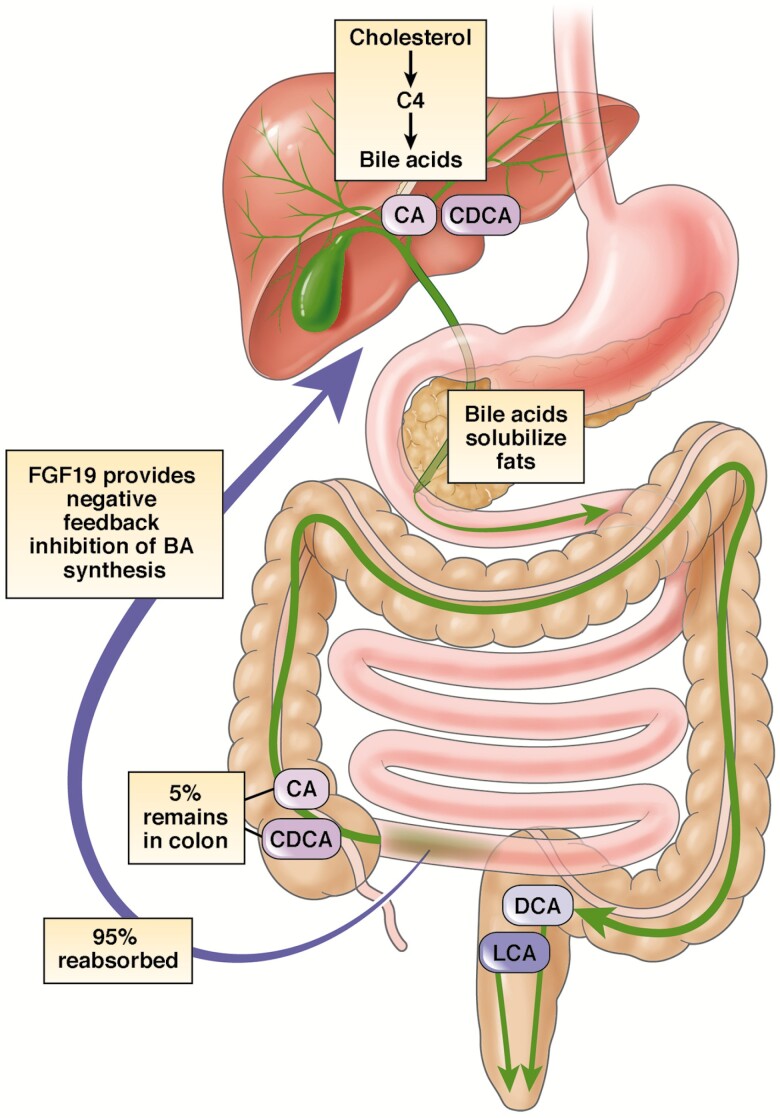
Bile acids are normal digestive chemicals made by the liver. They help absorb fat from food.
Normally:
- bile acids are released from the liver and gallbladder into the intestine after meals
- about 95% are reabsorbed in the last part of the small bowel (the terminal ileum)
- they are then recycled back to the liver and used again
Small amounts reaching the colon are normal and helpful. Bile acids naturally help regulate water secretion and bowel movement, helping keep stools soft and easy to pass.
Bile acid diarrhoea occurs when too many bile acids reach the colon, or when the colon is unusually sensitive to otherwise normal amounts of bile acids.
This can:
- draw excess water into the bowel
- speed up bowel movement
- cause urgency, watery diarrhoea and difficulty controlling stools
This condition is called bile acid diarrhoea (also called bile salt diarrhoea or bile acid malabsorption).
Bile acid diarrhoea is a problem of bile acid handling rather than structural bowel damage. Because the bowel lining often looks normal, tests such as colonoscopy, scans and stool inflammation markers are frequently normal even when bile acids are causing real symptoms.
Because it helps firm up stool, cholestyramine is also sometimes used to improve bowel control and reduce accidental leakage, even when bile acid diarrhoea is not clearly proven.
Getting the best from cholestyramine (Questran Lite®)
A practical guide to using cholestyramine for bile acid diarrhoea — what bile acids normally do, how the medicine helps, how to find the right dose, and how to fit it safely around your other medicines.
Begin with a small dose and build up gradually only if your stools remain loose.
Mix the powder thoroughly with fluid or a suitable soft food. Never swallow it dry.
Take other medicines at least 1 hour before or 4–6 hours after Questran Lite.
The goal is the lowest dose that gives comfortable, formed and predictable stools.
The reassuring bit
Bile acids are normal — and useful
Bile acids are normal digestive chemicals made by the liver. They are essential for digestion and help your body absorb fat from food.
Normally:
- bile acids enter the intestine, particularly after meals
- they help digest and absorb fat in the small bowel
- about 95% are reabsorbed near the end of the small bowel, called the terminal ileum
- they are then recycled back to the liver and used again
A small amount normally reaches the large bowel. This is normal and helpful.
Bile acids naturally encourage the bowel to secrete a little water and keep things moving. You can think of this as a gentle natural laxative effect that helps keep stools soft and easy to pass.
The problem in bile acid diarrhoea is not that bile acids are dangerous. It is that too much of this normal effect is occurring.
What goes wrong?
Bile acid diarrhoea can occur when:
- too many bile acids reach the large bowel, or
- the large bowel is unusually sensitive to their effects.
When this happens, bile acids can:
- draw too much water into the bowel
- make the bowel move too quickly
- cause loose or watery stools
- cause urgency
- make bowel motions harder to control
This is called bile acid diarrhoea. You may also hear the terms bile salt diarrhoea or bile acid malabsorption.
Importantly, this is usually a problem of bile acid handling rather than damage to the bowel. The bowel lining can look completely normal even when bile acids are causing significant symptoms.
Why me?
Why bile acid diarrhoea happens
There are several common patterns. Sometimes there is an obvious reason. Sometimes there is not.
Crohn's disease or surgery involving the terminal ileum
This is where most bile acids are normally reabsorbed. Inflammation, scarring or removal of this part of the bowel can allow more bile acids to reach the colon.
After gallbladder removal
Removing the gallbladder changes the pattern of bile delivery into the intestine. Some people subsequently develop diarrhoea, particularly after meals.
After radiotherapy
Radiotherapy involving the small bowel or pelvis can interfere with the normal reabsorption of bile acids.
Alongside another gut condition
Bile acid diarrhoea can occur with conditions such as coeliac disease, microscopic colitis and some pancreatic or small-bowel disorders.
Diarrhoea-type IBS
Around one-quarter to one-third of people otherwise labelled as having diarrhoea-predominant IBS or functional diarrhoea may have bile acid diarrhoea contributing to their symptoms.
Sometimes there is no obvious cause
The body's feedback system controlling bile acid production can become dysregulated, so the liver produces more bile acid than the intestine can comfortably recycle. This is called primary bile acid diarrhoea.
Why were my tests normal?
Routine tests can be completely normal
Bile acid diarrhoea is mainly a problem of bowel chemistry and bile acid handling rather than visible structural damage.
This means tests such as:
- colonoscopy
- CT or other scans
- faecal calprotectin or other stool inflammation markers
- routine blood tests
can all be normal. Normal results do not rule out bile acid diarrhoea.
Yes, although availability varies.
A specialised nuclear-medicine test called a SeHCAT scan measures how well the body retains and recycles bile acids.
A fasting blood test called C4 can provide information about how much bile acid the liver is producing.
A hormone called FGF19 is involved in the feedback system controlling bile acid production. It is useful in understanding the condition but is less established as a routine clinical test.
Where suitable testing is available it can help establish the diagnosis. Where it is not readily available, your doctor may use your symptoms, risk factors and sometimes a carefully managed treatment trial as part of the assessment.
The medicine
How cholestyramine helps
Cholestyramine is not absorbed into your bloodstream. It stays inside the intestine and binds bile acids.
This reduces the amount of active bile acid reaching the large bowel.
That can mean:
- less water entering the bowel
- firmer stools
- less urgency
- fewer bowel motions
- better bowel control
Because a formed stool is easier to hold than a liquid one, cholestyramine can also sometimes improve urgency, accidental leakage or faecal incontinence, even when bile acid diarrhoea has not been definitively proven.
The rule that matters most
Keep Questran Lite away from your other medicines
Cholestyramine works because it binds substances inside the bowel. Unfortunately, it can also bind some medicines and reduce how much of them your body absorbs.
Take your other medicines:
If you take several regular medicines, particularly medicines where maintaining a steady blood level is important, ask your doctor or pharmacist to help you build a practical schedule.
This separation is particularly important with medicines such as:
- thyroxine
- warfarin and some other anticoagulants
- digoxin
- anti-seizure medicines
- some transplant medicines
- the oral contraceptive pill
Other medicines can also be affected, so unless your doctor or pharmacist tells you otherwise, it is safest to apply the separation rule to all regular tablets.
Finding your dose
Start low and build up only if you need to
People vary greatly in how much cholestyramine they need. Starting gently makes bloating and constipation less likely.
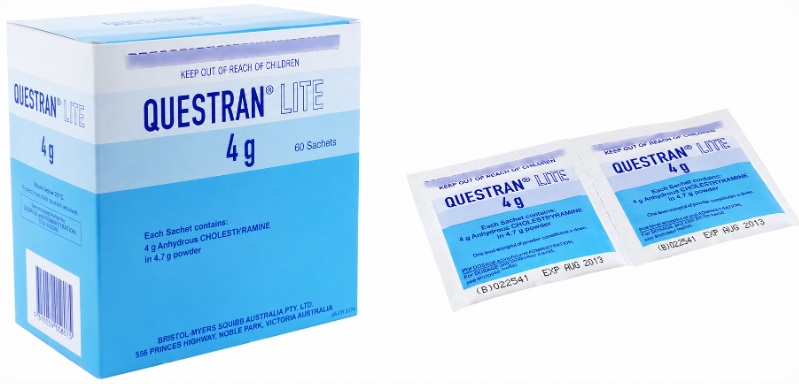
Each Questran Lite sachet contains 4 g of cholestyramine. Follow the dose your doctor has recommended.
Start gently
A common gradual-start approach is a small dose once or twice daily, particularly if you are prone to bloating.
Often ½ sachet once or twice dailyIncrease only while stools remain too loose
If there is not enough improvement and the medicine is well tolerated, the dose can be increased gradually.
Often by ½–1 sachet every 4–7 daysStop increasing once stools are comfortable
The aim is formed, comfortable and predictable stools with better urgency and control — not the highest dose you can tolerate.
Lowest dose that works for youEase back if stools become too firm
Constipation usually means you are now taking more than you need. Reduce the dose rather than pushing on.
How quickly should it work?
When cholestyramine is going to help bile acid diarrhoea, some improvement is often apparent within the first few days once an effective dose is being taken.
Finding your best dose can take longer because it is usually better to increase gradually.
If there has been no meaningful improvement despite taking it regularly at an adequate dose, simply continuing to increase it indefinitely is unlikely to be useful. The diagnosis or treatment should be reviewed.
Doses above 24 g a day require particular medical supervision because adverse effects become more likely.
Day to day
When and how to take it
When should I take it?
There is no single perfect time of day that suits everybody, and Questran Lite does not have to be taken immediately before a meal.
What matters most is that:
- you take it consistently
- the timing suits your bowel symptoms
- it fits your daily routine
- it is kept sufficiently far away from your other medicines
Some people find morning or daytime doses work well. Others may benefit from an evening dose if early-morning diarrhoea is particularly troublesome.
How do I mix it?
Never swallow Questran Lite as dry powder.
For a full 4 g sachet:
- Put approximately 100–150 mL of water or fruit juice into a glass or container.
- Add the powder.
- Stir vigorously until the mixture is evenly dispersed.
- Drink it.
- Add a little more fluid to the container, swirl it around and drink this as well so you receive the full dose.
The powder disperses rather than completely dissolves.
It can also be mixed with suitable moist foods such as:
- apple puree
- crushed fruit with plenty of moisture
- highly fluid soup
Some people find it more pleasant when it is chilled. Try not to breathe in the dry powder.
If you have been prescribed half a sachet: follow the measuring method recommended by your doctor or pharmacist, particularly if accurate dosing is important.
Alongside the medicine
Diet and fibre
Do I need a low-fat diet?
Fat entering the small bowel stimulates bile release. For some people, particularly large or very fatty meals therefore make symptoms worse.
If you notice this pattern, reducing the fattiest meals can help. Practical changes include:
- choosing leaner meat
- removing obvious fat and skin
- grilling, baking or steaming rather than frying
- reducing very oily meals
- going easy on large amounts of butter and cream
- using lower-fat dairy if high-fat dairy clearly triggers symptoms
You do not need to eliminate fat completely. The aim is a healthy, sustainable diet and to identify foods that genuinely make your own symptoms worse.
Yes, for some people. Soluble fibre works differently from cholestyramine and can help improve stool consistency.
Psyllium forms a gel that absorbs water and can help bulk and firm loose stools. A common starting amount is around 3.5–7 g daily.
Partially hydrolysed guar gum (PHGG) is another soluble fibre. It does not form the same thick gel and some people find it easier to tolerate if they are prone to bloating. A common starting amount is around 5 g daily.
If adding fibre:
- start with a small amount
- increase gradually
- drink adequate fluid
- change one thing at a time so you can tell what is helping
Large amounts of coarse insoluble fibre, such as wheat bran, can sometimes make diarrhoea or urgency worse.
Troubleshooting
What if it doesn't seem to work?
There are several possibilities:
- the dose may still be too low
- doses may be getting missed
- bloating or constipation may have limited dose increases
- the timing may be difficult around your other medicines
- the powder may simply be difficult to tolerate
- there may be another cause of diarrhoea as well
If a reasonable trial has genuinely not helped, do not simply continue increasing the dose indefinitely.
Your doctor may reconsider:
- whether bile acids are the main problem
- whether another bowel condition is contributing
- whether soluble fibre would help
- whether an anti-diarrhoeal medicine such as loperamide is appropriate
- whether another bile-acid binder should be considered
Other causes worth considering can include:
- microscopic colitis
- coeliac disease
- active Crohn's disease
- pancreatic insufficiency
- infection
- medication-related diarrhoea
- another functional bowel disorder
An alternative bile-acid binder called colesevelam is available as a tablet and is often easier to take than cholestyramine powder.
In Australia, colesevelam is not PBS-subsidised. Where an unapproved imported product is used, access generally requires your doctor to arrange approval through the TGA Special Access Scheme, usually Category B.
For this reason it is generally considered when cholestyramine has not worked adequately or cannot be tolerated, rather than as the routine first treatment.
What to watch for
Side effects and longer-term use
Constipation
This often means your dose is now more than you need. Reduce the dose rather than continuing to increase it.
The goal is a comfortable, formed stool — not a hard stool.
Bloating or wind
These are relatively common when cholestyramine is first started. Beginning with a smaller dose and increasing gradually usually improves tolerance.
If bloating is severe or persistent, speak with your doctor.
Vitamins with long-term use
Bile acids help the body absorb fat and the fat-soluble vitamins A, D, E and K.
Larger doses of cholestyramine used for a prolonged period can sometimes interfere with this process. It can also affect folate absorption.
This is particularly relevant if you already have problems absorbing nutrients because of bowel disease or surgery.
Routine vitamin testing is not necessary for everybody, but your doctor may check levels or recommend supplementation when there is a particular reason to do so.
Safety
When to contact your doctor
Arrange a review if:
- your diarrhoea suddenly becomes much worse
- you lose weight without trying
- you see blood in the stool
- bowel motions repeatedly wake you from sleep
- you develop persistent or significant abdominal pain
- constipation becomes troublesome
- a treatment that previously worked stops working
- you cannot find a dose that gives reasonable control
- you have taken an adequate dose without meaningful improvement
These features do not necessarily mean something serious is wrong, but they may mean the diagnosis or treatment needs to be reconsidered.
Seek urgent medical attention if:
- you have severe or rapidly worsening abdominal pain
- you have persistent vomiting with marked abdominal swelling or inability to open your bowels
- you vomit blood
- you pass black, tarry stools
- you have significant bleeding with weakness, faintness or collapse
In an emergency in Australia, call 000.
The key message
Cholestyramine can be very effective for bile acid diarrhoea, but there is no single correct dose for everybody.
- start with a small dose
- increase gradually only while stools remain too loose
- stop increasing once stools are comfortable and formed
- use the lowest dose that keeps symptoms controlled
- always mix the powder before taking it
- keep it well separated from your other medicines
- reduce particularly fatty meals if they clearly trigger symptoms
- have persistent symptoms reviewed rather than simply continuing to increase the dose
The aim is not simply to stop diarrhoea. It is to achieve comfortable, predictable bowel motions with less urgency and better confidence and control in everyday life.